







Expo
view channel
view channel
view channel
view channel
view channel
view channel
view channel
view channel
AICritical CareSurgical TechniquesPatient Care
Health ITPoint of CareBusiness
Events
Webinars

- Anatomical Guidance System Improves Trauma Ultrasound Acquisition by Novice Users
- AI-Enhanced Handheld Ultrasound Improves Carotid Plaque Detection
- Noninvasive Imaging Approach Aims to Detect Basal Cell Carcinoma Before It Becomes Visible
- New Sensor Could Bring Contactless Vital Sign Monitoring to Hospital Bedsides
- Emergency Department Campaign Reduces CT Use Without Identified Missed Injuries
- Handheld Device Improves Targeted Cell Collection for Early Ovarian Cancer Assessment
- Light-Activated Nanoparticles May Offer New Approach to Retinal Prostheses
- FDA Approves First Sirolimus Drug-Eluting Balloon for Coronary In-Stent Restenosis
- Handheld Infrared Imaging Device Supports Tumor Margin Assessment During Surgery
- Needle-Free Intrauterine Anesthesia Technique Reduces Pain During IUD Insertion
- Virtual Reality Helps Claustrophobic Patients Complete Cardiac PET/CT Scans
- Weighted Blankets Reduce Anxiety in Hospitalized Adults
- Multicenter Study Quantifies Delays in Care for Emergency Department Boarders
- Real-Time Radiation Monitor Supports Safer Fluoroscopy-Guided Procedures
- FDA-Cleared Finger Cuff Device Enables Home Blood Pressure Monitoring
- AI Tool Integrates MRI and Ultrasound to Detect Endometriosis
- New MRI Index Reveals How Brain Blood Flow Supports Cellular Energy Needs
- Structure-Aware AI Aims to Improve Reliability of Medical Image Analysis
- PSMA PET/CT Helps Guide Pre-Biopsy Decisions in Prostate Cancer
- AI Models Evaluated for Spotting Ischemic Stroke Lesions on Routine MRI
- Robotic Single-Port System Gains CE Mark for Transvaginal Gynecologic Procedures
- Smartphone-Integrated Epinephrine Auto-Injector Concept Wins Red Dot Design Award
- First U.S. Commercial Cases Demonstrate New Approach to Transseptal Access
- FDA Approval Clears Path for BCI Integration with Personal Computing Devices
- Partnership Advances AI Tool for Predicting Malignant Cerebral Edema
- Smartphone App Improves Blood Pressure Control in Hypertension
- Registry-Driven Digital Outreach Boosts Use of Heart Failure Medicines
- Nurse-Coordinated Care Model Improves Heart Failure Outcomes
- Imaging Tool Quantifies Calcinosis Cutis Volume to Monitor Treatment
- Digital Symptom Monitoring Supports More Personalized Breast Cancer Care
- AI Improves Non-Contrast CT Interpretation for Time-Sensitive Stroke Assessment
- AI-Powered ECG Model Gains FDA Authorization for Emergency Cardiac Assessment
- Explainable AI Tool Identifies High-Risk Patients Before Heart Attack Reperfusion
- AI Tools Show Potential to Detect Subtle Signs of Interval Breast Cancer
- AI Framework Aims to Turn Medical Care from Reactive to Preventive
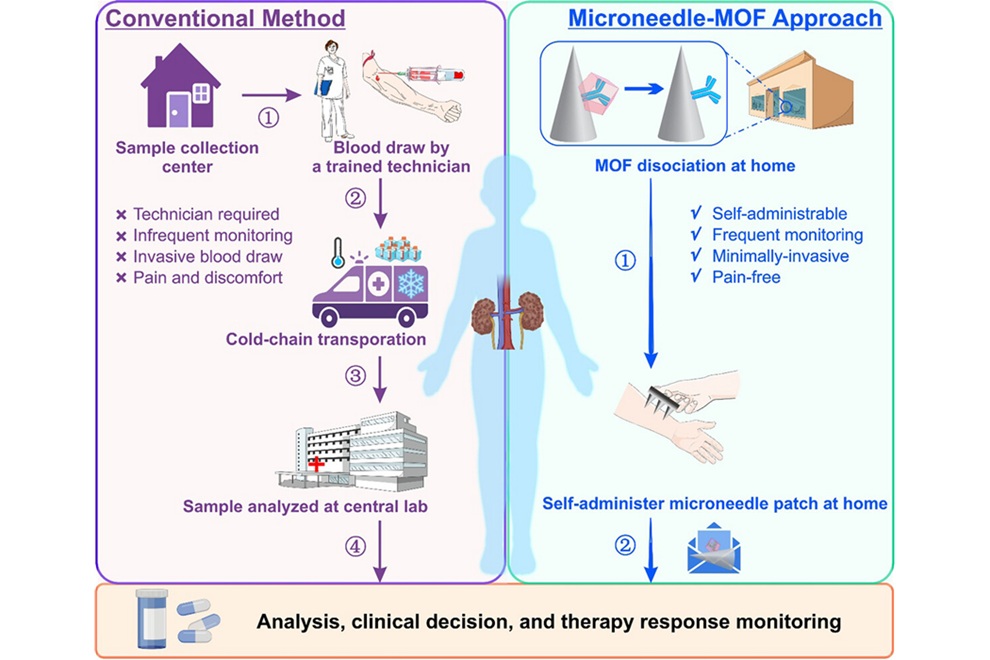
- Microneedle Patch Enables At-Home Monitoring of Acute Kidney Injury
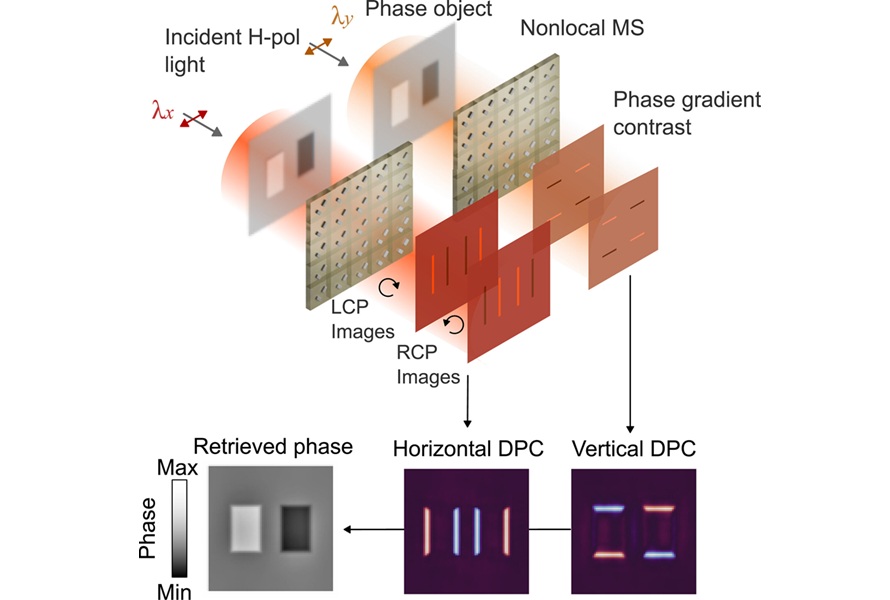
- Ultrathin Metasurface Could Bring Quantitative Phase Imaging to Portable Devices
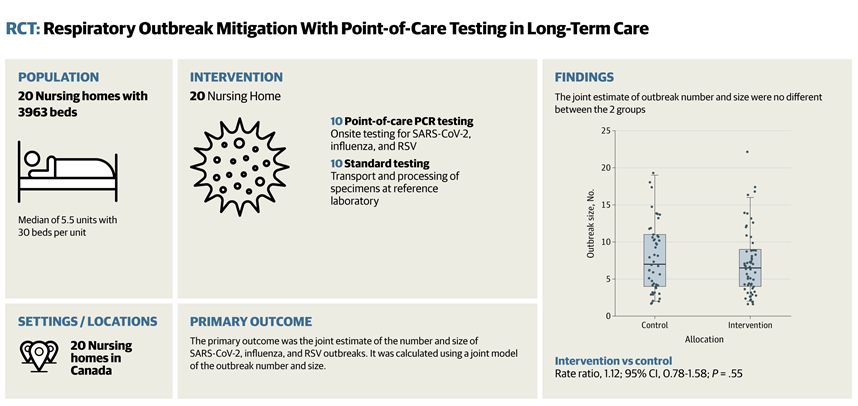
- Rapid Onsite Testing Reduces Emergency Department Transfers in Long-Term Care
- New Brain Ultrasound Platform Enables Bedside Postoperative Imaging
- Handheld Ultrasound Expands Point-of-Care Imaging Access in Brazil
 Expo
- Anatomical Guidance System Improves Trauma Ultrasound Acquisition by Novice Users
- AI-Enhanced Handheld Ultrasound Improves Carotid Plaque Detection
- Noninvasive Imaging Approach Aims to Detect Basal Cell Carcinoma Before It Becomes Visible
- New Sensor Could Bring Contactless Vital Sign Monitoring to Hospital Bedsides
- Emergency Department Campaign Reduces CT Use Without Identified Missed Injuries
- Handheld Device Improves Targeted Cell Collection for Early Ovarian Cancer Assessment
- Light-Activated Nanoparticles May Offer New Approach to Retinal Prostheses
- FDA Approves First Sirolimus Drug-Eluting Balloon for Coronary In-Stent Restenosis
- Handheld Infrared Imaging Device Supports Tumor Margin Assessment During Surgery
- Needle-Free Intrauterine Anesthesia Technique Reduces Pain During IUD Insertion
- Virtual Reality Helps Claustrophobic Patients Complete Cardiac PET/CT Scans
- Weighted Blankets Reduce Anxiety in Hospitalized Adults
- Multicenter Study Quantifies Delays in Care for Emergency Department Boarders
- Real-Time Radiation Monitor Supports Safer Fluoroscopy-Guided Procedures
- FDA-Cleared Finger Cuff Device Enables Home Blood Pressure Monitoring
- AI Tool Integrates MRI and Ultrasound to Detect Endometriosis
- New MRI Index Reveals How Brain Blood Flow Supports Cellular Energy Needs
- Structure-Aware AI Aims to Improve Reliability of Medical Image Analysis
- PSMA PET/CT Helps Guide Pre-Biopsy Decisions in Prostate Cancer
- AI Models Evaluated for Spotting Ischemic Stroke Lesions on Routine MRI
- Robotic Single-Port System Gains CE Mark for Transvaginal Gynecologic Procedures
- Smartphone-Integrated Epinephrine Auto-Injector Concept Wins Red Dot Design Award
- First U.S. Commercial Cases Demonstrate New Approach to Transseptal Access
- FDA Approval Clears Path for BCI Integration with Personal Computing Devices
- Partnership Advances AI Tool for Predicting Malignant Cerebral Edema
- Smartphone App Improves Blood Pressure Control in Hypertension
- Registry-Driven Digital Outreach Boosts Use of Heart Failure Medicines
- Nurse-Coordinated Care Model Improves Heart Failure Outcomes
- Imaging Tool Quantifies Calcinosis Cutis Volume to Monitor Treatment
- Digital Symptom Monitoring Supports More Personalized Breast Cancer Care
- AI Improves Non-Contrast CT Interpretation for Time-Sensitive Stroke Assessment
- AI-Powered ECG Model Gains FDA Authorization for Emergency Cardiac Assessment
- Explainable AI Tool Identifies High-Risk Patients Before Heart Attack Reperfusion
- AI Tools Show Potential to Detect Subtle Signs of Interval Breast Cancer
- AI Framework Aims to Turn Medical Care from Reactive to Preventive
- Microneedle Patch Enables At-Home Monitoring of Acute Kidney Injury
- Ultrathin Metasurface Could Bring Quantitative Phase Imaging to Portable Devices
- Rapid Onsite Testing Reduces Emergency Department Transfers in Long-Term Care
- New Brain Ultrasound Platform Enables Bedside Postoperative Imaging
- Handheld Ultrasound Expands Point-of-Care Imaging Access in Brazil






















 Client Login
