







Expo
view channel
view channel
view channel
view channel
view channel
view channel
view channel
view channel
AICritical Care
Patient CareMedical ImagingHealth ITPoint of CareBusiness
Events
Webinars

- FDA Clears Multi-Device ECG Analysis Software for Extended Monitoring
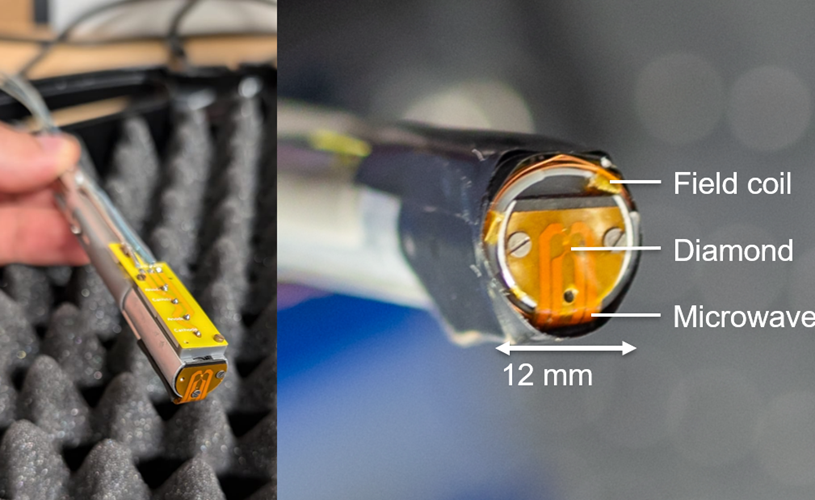
- Diamond-Based Magnetometers Could Enable New Approaches to Heart Monitoring
- Portable Artificial Lung Technology Could Reshape Care for Chronic Lung Disease
- Multimodal AI Improves Treatment Response Prediction in Lung Cancer
- New Approach Helps Identify Materials for More Reliable Wearable Electronics
- Needle-Free Intrauterine Anesthesia Technique Reduces Pain During IUD Insertion
- Robotic Platform Advances Fetoscopic Treatment of Twin-to-Twin Transfusion Syndrome
- Patient-Specific AI Tool Aligns X-Rays With 3D Scans For Surgical Navigation
- Hydrogel Dermal Supports Healing of Complex Wounds After Cancer Surgery
- FDA Clears Integrated Platform for Real-Time Cardiac Imaging and Catheter Guidance
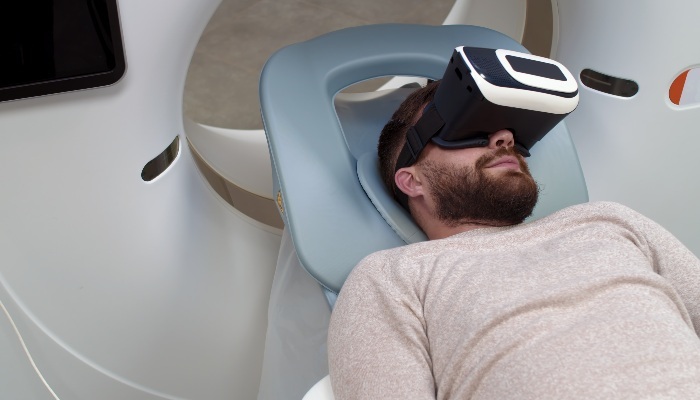
- Virtual Reality Helps Claustrophobic Patients Complete Cardiac PET/CT Scans
- Weighted Blankets Reduce Anxiety in Hospitalized Adults
- Multicenter Study Quantifies Delays in Care for Emergency Department Boarders
- Real-Time Radiation Monitor Supports Safer Fluoroscopy-Guided Procedures
- FDA-Cleared Finger Cuff Device Enables Home Blood Pressure Monitoring
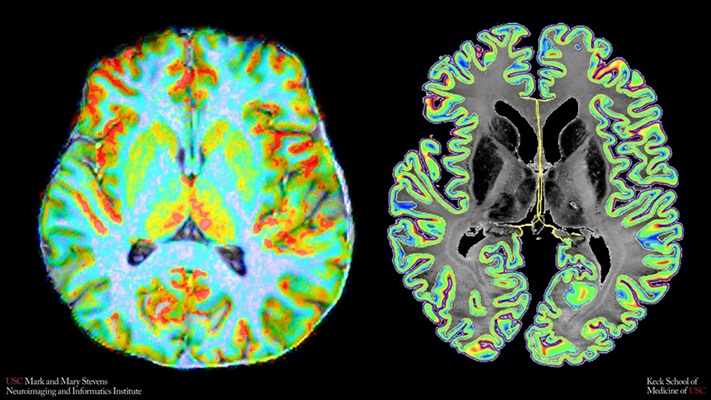
- New MRI Index Reveals How Brain Blood Flow Supports Cellular Energy Needs
- Structure-Aware AI Aims to Improve Reliability of Medical Image Analysis
- PSMA PET/CT Helps Guide Pre-Biopsy Decisions in Prostate Cancer
- AI Models Evaluated for Spotting Ischemic Stroke Lesions on Routine MRI
- Noninvasive MRI Spectroscopy Classifies Pediatric Medulloblastoma Molecular Subgroups
- Robotic Single-Port System Gains CE Mark for Transvaginal Gynecologic Procedures
- Smartphone-Integrated Epinephrine Auto-Injector Concept Wins Red Dot Design Award
- First U.S. Commercial Cases Demonstrate New Approach to Transseptal Access
- FDA Approval Clears Path for BCI Integration with Personal Computing Devices
- Partnership Advances AI Tool for Predicting Malignant Cerebral Edema
- Smartphone App Improves Blood Pressure Control in Hypertension
- Registry-Driven Digital Outreach Boosts Use of Heart Failure Medicines
- Nurse-Coordinated Care Model Improves Heart Failure Outcomes
- Imaging Tool Quantifies Calcinosis Cutis Volume to Monitor Treatment
- Digital Symptom Monitoring Supports More Personalized Breast Cancer Care
- AI-Powered ECG Model Gains FDA Authorization for Emergency Cardiac Assessment
- Explainable AI Tool Identifies High-Risk Patients Before Heart Attack Reperfusion
- AI Tools Show Potential to Detect Subtle Signs of Interval Breast Cancer
- AI Framework Aims to Turn Medical Care from Reactive to Preventive
- AI Model Predicts Indwelling Catheter Use After Spinal Cord Injury
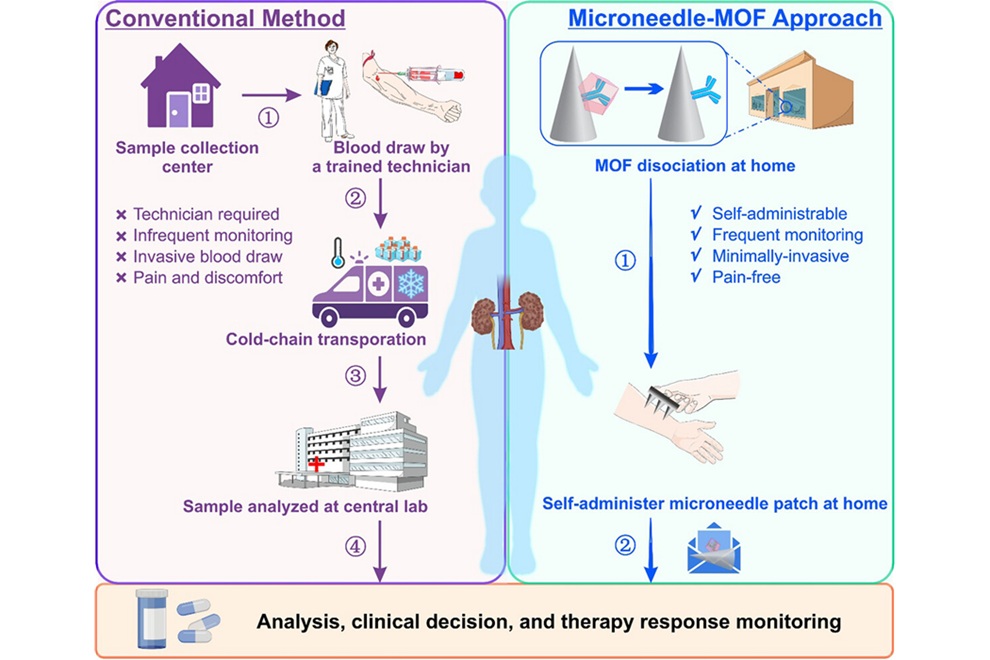
- Microneedle Patch Enables At-Home Monitoring of Acute Kidney Injury
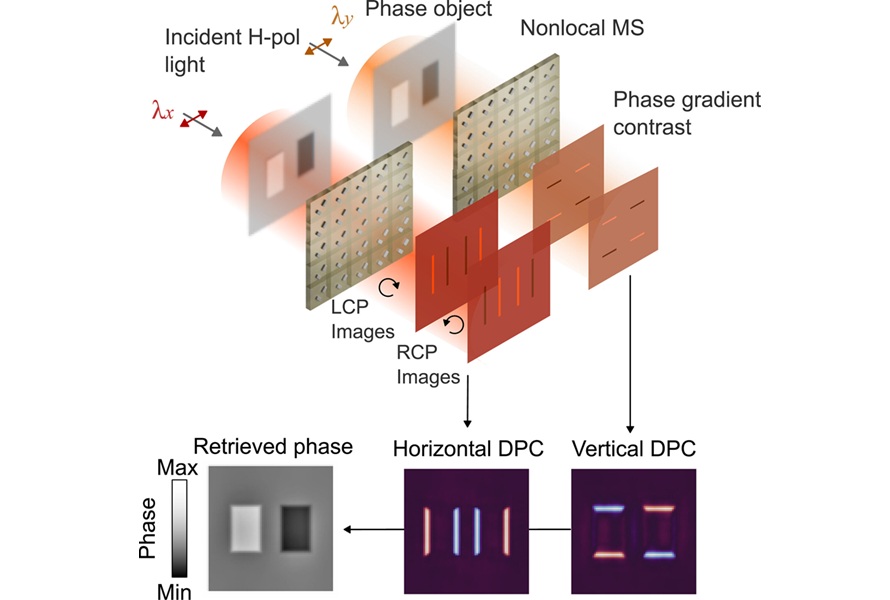
- Ultrathin Metasurface Could Bring Quantitative Phase Imaging to Portable Devices
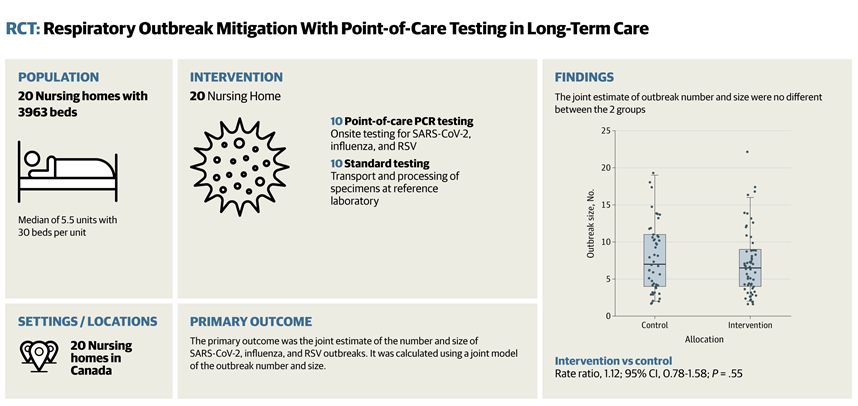
- Rapid Onsite Testing Reduces Emergency Department Transfers in Long-Term Care
- New Brain Ultrasound Platform Enables Bedside Postoperative Imaging
- Handheld Ultrasound Expands Point-of-Care Imaging Access in Brazil
 Expo
- FDA Clears Multi-Device ECG Analysis Software for Extended Monitoring
- Diamond-Based Magnetometers Could Enable New Approaches to Heart Monitoring
- Portable Artificial Lung Technology Could Reshape Care for Chronic Lung Disease
- Multimodal AI Improves Treatment Response Prediction in Lung Cancer
- New Approach Helps Identify Materials for More Reliable Wearable Electronics
- Needle-Free Intrauterine Anesthesia Technique Reduces Pain During IUD Insertion
- Robotic Platform Advances Fetoscopic Treatment of Twin-to-Twin Transfusion Syndrome
- Patient-Specific AI Tool Aligns X-Rays With 3D Scans For Surgical Navigation
- Hydrogel Dermal Supports Healing of Complex Wounds After Cancer Surgery
- FDA Clears Integrated Platform for Real-Time Cardiac Imaging and Catheter Guidance
- Virtual Reality Helps Claustrophobic Patients Complete Cardiac PET/CT Scans
- Weighted Blankets Reduce Anxiety in Hospitalized Adults
- Multicenter Study Quantifies Delays in Care for Emergency Department Boarders
- Real-Time Radiation Monitor Supports Safer Fluoroscopy-Guided Procedures
- FDA-Cleared Finger Cuff Device Enables Home Blood Pressure Monitoring
- New MRI Index Reveals How Brain Blood Flow Supports Cellular Energy Needs
- Structure-Aware AI Aims to Improve Reliability of Medical Image Analysis
- PSMA PET/CT Helps Guide Pre-Biopsy Decisions in Prostate Cancer
- AI Models Evaluated for Spotting Ischemic Stroke Lesions on Routine MRI
- Noninvasive MRI Spectroscopy Classifies Pediatric Medulloblastoma Molecular Subgroups
- Robotic Single-Port System Gains CE Mark for Transvaginal Gynecologic Procedures
- Smartphone-Integrated Epinephrine Auto-Injector Concept Wins Red Dot Design Award
- First U.S. Commercial Cases Demonstrate New Approach to Transseptal Access
- FDA Approval Clears Path for BCI Integration with Personal Computing Devices
- Partnership Advances AI Tool for Predicting Malignant Cerebral Edema
- Smartphone App Improves Blood Pressure Control in Hypertension
- Registry-Driven Digital Outreach Boosts Use of Heart Failure Medicines
- Nurse-Coordinated Care Model Improves Heart Failure Outcomes
- Imaging Tool Quantifies Calcinosis Cutis Volume to Monitor Treatment
- Digital Symptom Monitoring Supports More Personalized Breast Cancer Care
- AI-Powered ECG Model Gains FDA Authorization for Emergency Cardiac Assessment
- Explainable AI Tool Identifies High-Risk Patients Before Heart Attack Reperfusion
- AI Tools Show Potential to Detect Subtle Signs of Interval Breast Cancer
- AI Framework Aims to Turn Medical Care from Reactive to Preventive
- AI Model Predicts Indwelling Catheter Use After Spinal Cord Injury
- Microneedle Patch Enables At-Home Monitoring of Acute Kidney Injury
- Ultrathin Metasurface Could Bring Quantitative Phase Imaging to Portable Devices
- Rapid Onsite Testing Reduces Emergency Department Transfers in Long-Term Care
- New Brain Ultrasound Platform Enables Bedside Postoperative Imaging
- Handheld Ultrasound Expands Point-of-Care Imaging Access in Brazil


























 Client Login
