







Expo
view channel
view channel
view channel
view channel
view channel
view channel
view channel
view channel
AICritical Care
Patient CareMedical ImagingHealth ITPoint of CareBusiness
Events
Webinars

- Nasal Spray Provides Rapid Pain Relief for Children in Emergency Care
- Noninvasive AI Tool Maps Atrial Cardiomyopathy to Support Ablation Planning
- Bioelectronic Network Enables Devices to Communicate Through Body Tissue and Coordinate Therapy
- AI Platform Screens for Amyloid Cardiomyopathy Using ECG Images
- Noninvasive Contact Lens Sensor Detects Tear Serotonin for Stress Assessment
- Ultra-Low-Dose Radiotherapy Relieves Myeloma Bone Pain in Trial
- Labor Induction Guide Improves Patient Satisfaction in Randomized Trial
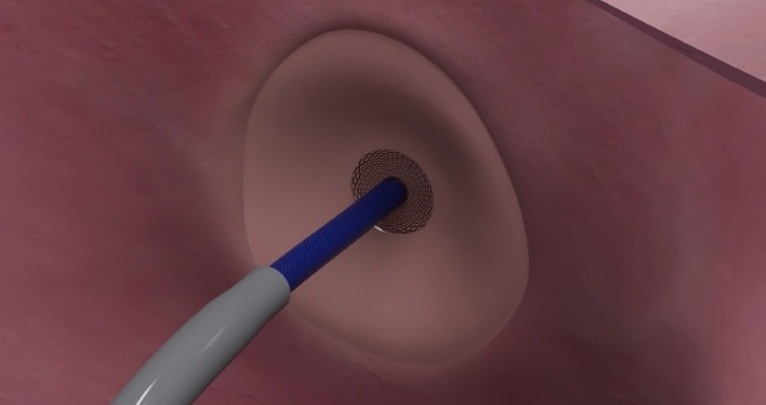
- First Human Implant Performed With New Open Mitral Annuloplasty Ring
- Handheld Device Improves Targeted Cell Collection for Early Ovarian Cancer Assessment
- Light-Activated Nanoparticles May Offer New Approach to Retinal Prostheses
- EHR Model Flags High-Risk Periods in Patients with Metastatic Breast Cancer
- Virtual Reality Helps Claustrophobic Patients Complete Cardiac PET/CT Scans
- Weighted Blankets Reduce Anxiety in Hospitalized Adults
- Multicenter Study Quantifies Delays in Care for Emergency Department Boarders
- Real-Time Radiation Monitor Supports Safer Fluoroscopy-Guided Procedures
- MRI-Based Test Speeds Multiple Sclerosis Diagnosis and Reduces Lumbar Punctures
- AI Tool Improves Early Detection of Silicosis and Black Lung on X-Rays
- New MRI Approach Captures Rapidly Decaying Tissue Signals
- AI Tool Integrates MRI and Ultrasound to Detect Endometriosis
- New MRI Index Reveals How Brain Blood Flow Supports Cellular Energy Needs
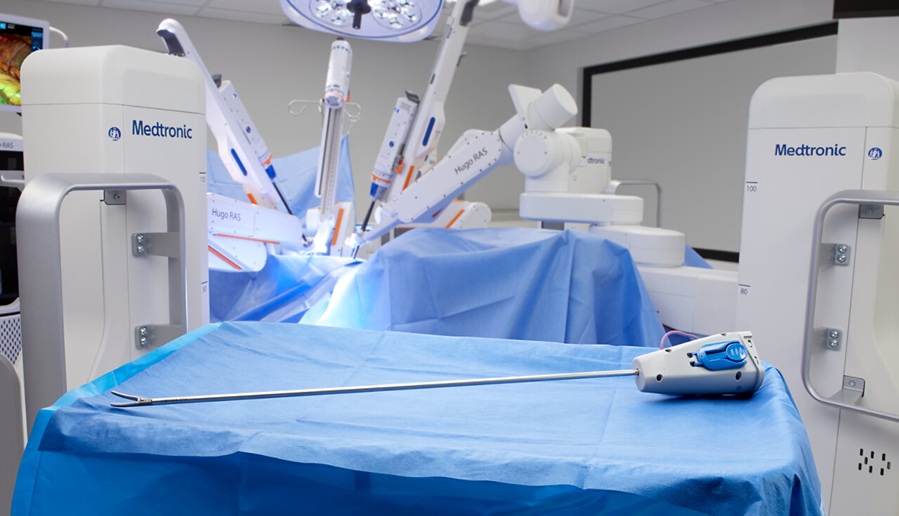
- Robotic Single-Port System Gains CE Mark for Transvaginal Gynecologic Procedures
- Smartphone-Integrated Epinephrine Auto-Injector Concept Wins Red Dot Design Award
- First U.S. Commercial Cases Demonstrate New Approach to Transseptal Access
- FDA Approval Clears Path for BCI Integration with Personal Computing Devices
- Partnership Advances AI Tool for Predicting Malignant Cerebral Edema
- Healthcare Database Helps Close Long COVID Surveillance Gap
- New Tablet Platform Extends Stroke Neurorehabilitation Beyond the Clinic
- Smartphone App Improves Blood Pressure Control in Hypertension
- Registry-Driven Digital Outreach Boosts Use of Heart Failure Medicines
- Nurse-Coordinated Care Model Improves Heart Failure Outcomes
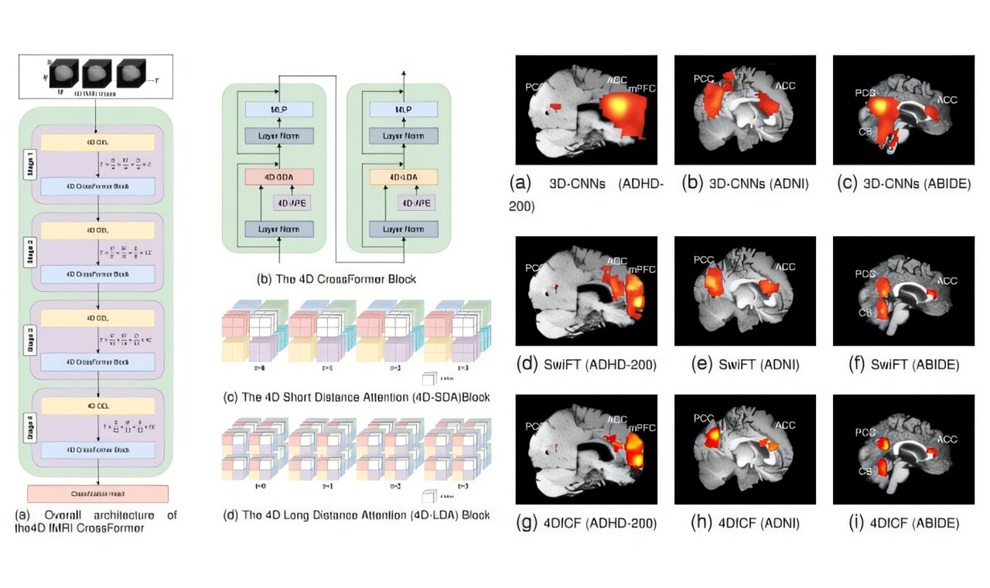
- Explainable AI Tool Improves Brain Disorder Screening from 4D fMRI
- AI Improves Non-Contrast CT Interpretation for Time-Sensitive Stroke Assessment
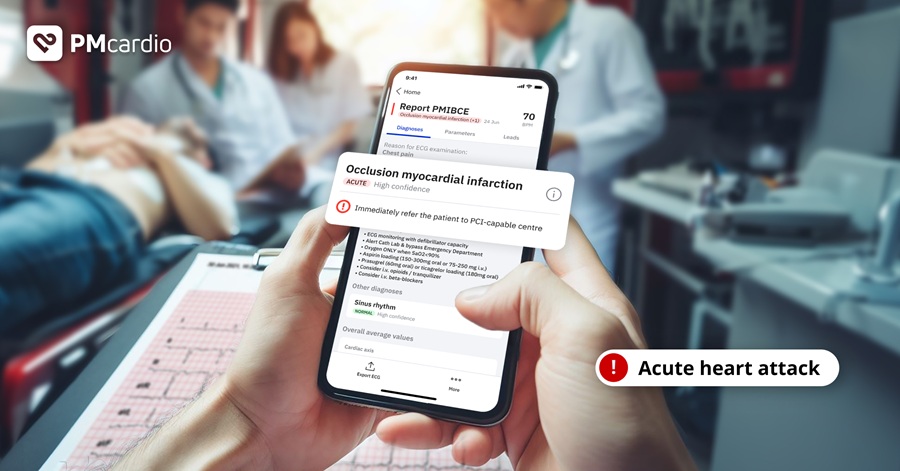
- AI-Powered ECG Model Gains FDA Authorization for Emergency Cardiac Assessment
- Explainable AI Tool Identifies High-Risk Patients Before Heart Attack Reperfusion
- AI Tools Show Potential to Detect Subtle Signs of Interval Breast Cancer
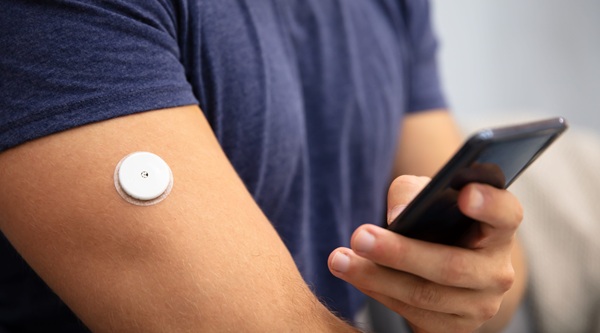
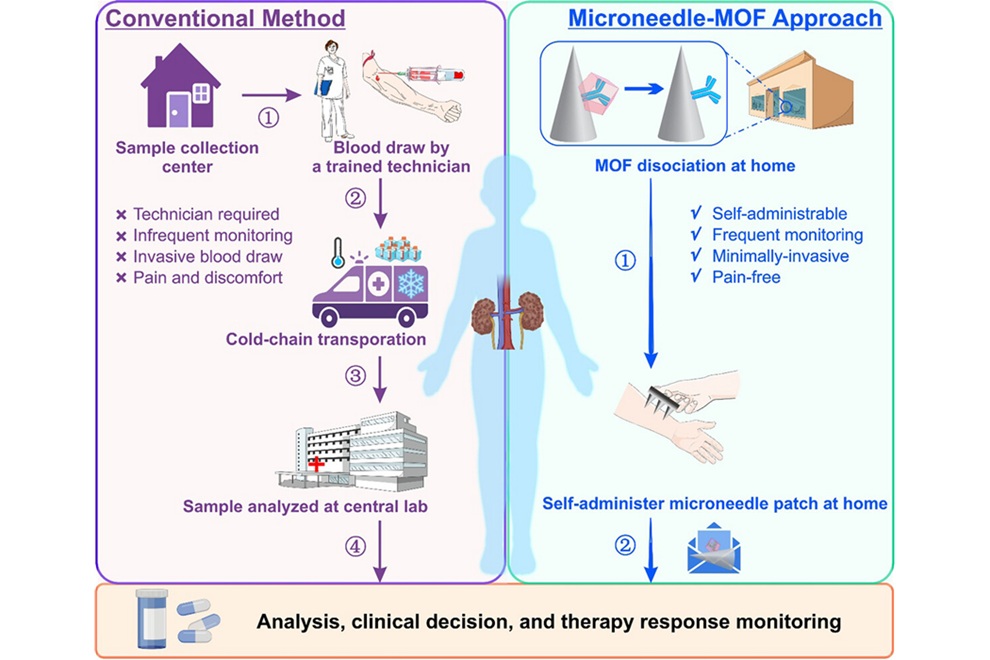
- Microneedle Patch Enables At-Home Monitoring of Acute Kidney Injury
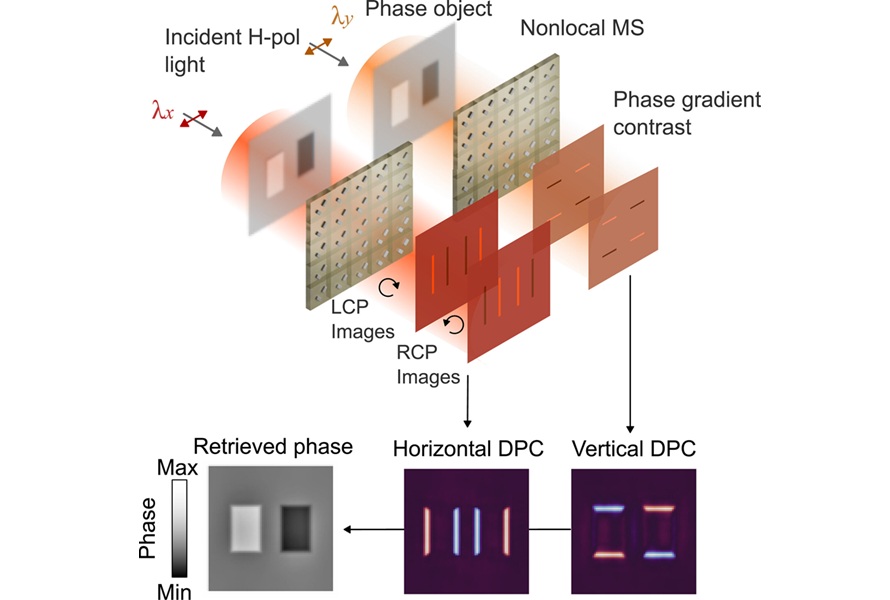
- Ultrathin Metasurface Could Bring Quantitative Phase Imaging to Portable Devices
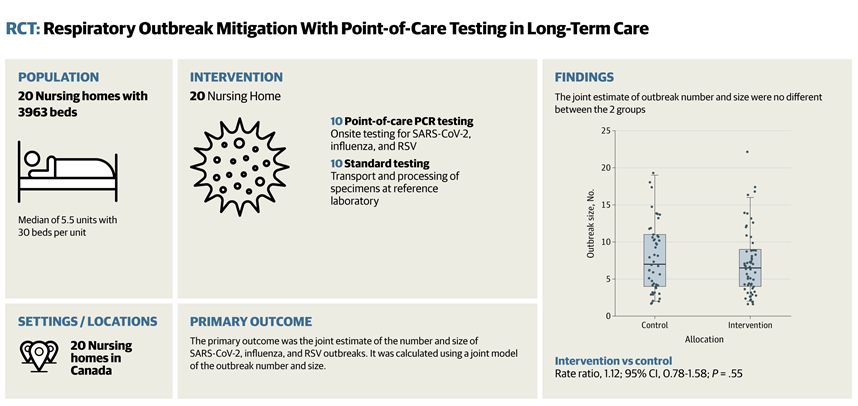
- Rapid Onsite Testing Reduces Emergency Department Transfers in Long-Term Care
- New Brain Ultrasound Platform Enables Bedside Postoperative Imaging
- Handheld Ultrasound Expands Point-of-Care Imaging Access in Brazil
 Expo
- Nasal Spray Provides Rapid Pain Relief for Children in Emergency Care
- Noninvasive AI Tool Maps Atrial Cardiomyopathy to Support Ablation Planning
- Bioelectronic Network Enables Devices to Communicate Through Body Tissue and Coordinate Therapy
- AI Platform Screens for Amyloid Cardiomyopathy Using ECG Images
- Noninvasive Contact Lens Sensor Detects Tear Serotonin for Stress Assessment
- Ultra-Low-Dose Radiotherapy Relieves Myeloma Bone Pain in Trial
- Labor Induction Guide Improves Patient Satisfaction in Randomized Trial
- First Human Implant Performed With New Open Mitral Annuloplasty Ring
- Handheld Device Improves Targeted Cell Collection for Early Ovarian Cancer Assessment
- Light-Activated Nanoparticles May Offer New Approach to Retinal Prostheses
- EHR Model Flags High-Risk Periods in Patients with Metastatic Breast Cancer
- Virtual Reality Helps Claustrophobic Patients Complete Cardiac PET/CT Scans
- Weighted Blankets Reduce Anxiety in Hospitalized Adults
- Multicenter Study Quantifies Delays in Care for Emergency Department Boarders
- Real-Time Radiation Monitor Supports Safer Fluoroscopy-Guided Procedures
- MRI-Based Test Speeds Multiple Sclerosis Diagnosis and Reduces Lumbar Punctures
- AI Tool Improves Early Detection of Silicosis and Black Lung on X-Rays
- New MRI Approach Captures Rapidly Decaying Tissue Signals
- AI Tool Integrates MRI and Ultrasound to Detect Endometriosis
- New MRI Index Reveals How Brain Blood Flow Supports Cellular Energy Needs
- Robotic Single-Port System Gains CE Mark for Transvaginal Gynecologic Procedures
- Smartphone-Integrated Epinephrine Auto-Injector Concept Wins Red Dot Design Award
- First U.S. Commercial Cases Demonstrate New Approach to Transseptal Access
- FDA Approval Clears Path for BCI Integration with Personal Computing Devices
- Partnership Advances AI Tool for Predicting Malignant Cerebral Edema
- Healthcare Database Helps Close Long COVID Surveillance Gap
- New Tablet Platform Extends Stroke Neurorehabilitation Beyond the Clinic
- Smartphone App Improves Blood Pressure Control in Hypertension
- Registry-Driven Digital Outreach Boosts Use of Heart Failure Medicines
- Nurse-Coordinated Care Model Improves Heart Failure Outcomes
- Explainable AI Tool Improves Brain Disorder Screening from 4D fMRI
- AI Improves Non-Contrast CT Interpretation for Time-Sensitive Stroke Assessment
- AI-Powered ECG Model Gains FDA Authorization for Emergency Cardiac Assessment
- Explainable AI Tool Identifies High-Risk Patients Before Heart Attack Reperfusion
- AI Tools Show Potential to Detect Subtle Signs of Interval Breast Cancer
- Microneedle Patch Enables At-Home Monitoring of Acute Kidney Injury
- Ultrathin Metasurface Could Bring Quantitative Phase Imaging to Portable Devices
- Rapid Onsite Testing Reduces Emergency Department Transfers in Long-Term Care
- New Brain Ultrasound Platform Enables Bedside Postoperative Imaging
- Handheld Ultrasound Expands Point-of-Care Imaging Access in Brazil























 Client Login
